
April 2026
Unsurprisingly, I require plastic surgery on the wound: a skin graft.
The good news: it can be done under a local anaesthetic. Day case.
The bad news: I bet this is gonna hurt when that local wears off. A lot!
I am looking forward to two big events this summer. The first is my online conversation with @mkirschenbaum.bsky.social as part of the SHARPIES festival, organised by SHARP.
The second is that I am keynoting the ACM Hypertext 2026 conference and hope/plan to do this in-person, in London. More soon.
Both of these depend upon my health situation. Things are up in the air right now. I am about to commence IV feeding (parenteral nutrition) with complex logistics. They also depend on me not losing any more weight, because if I do, I might disappear.
Today, I am travelling to Guy's Hospital to plan plastic surgery on my leg, for the bite wound.
“It is a devastating indictment of the impartiality and competence of the OfS, implicating its operations, leadership, governance and strategy. It raises important and urgent questions for the government" - VC of Sussex, quoted in Research Professional Playbook on the legal judgement against OfS
OfS overstepped their jurisdiction and don't seem even to understand what they are allowed to regulate.
More than a head should roll. The whole organisation needs to go.
Antibiotics are an economic failure. Terrible that we need view these lifesaving drugs through such a lens. https://press.asimov.com/articles/antibiotics-failure
Just read that "Musk says he felt that OpenAI's founders took advantage of his money, reputation, and guidance to get the startup off the ground" and he is suing OpenAI. Sure he's got the money. But "reputation"...
I spoke today with the hospital. They told me that I require IV nutritional support. This, though, will be the slightly lesser version, administered during my dialysis, rather than through a new line. This means I must now go to hospital 3x per week for haemodialysis instead of doing it at home.
This is logistically terrible. So much of my life will be spent doing dialysis. But I feel terrible and need to be able to fight this norovirus. Putting on weight is the key to this. So I must go along with the process.
I find it very frustrating when people announce new versions of software they have produced, with no information on what the software is or does. Assuming people already know.
"Pleased to announce v0.1.2 of Darkwing. This version brings Capybara integration and Dingbat rollback support!"
Detective work on the cover of Thomas Pynchon's Shadow Ticket
https://andraskisery.substack.com/p/the-cover-of-shadow-ticket?utm_id=97758_v0_s00_e223_tv0
https://www.theguardian.com/us-news/2026/apr/27/jam-master-jay-run-dmc-killing
I look at English higher education, and its destruction by this government and those before it, and feel such melancholy sadness. They have torn down something wonderful. They have hurt so many good people, who only wanted careers teaching and researching.
Lecturer in Digital and Immersive Storytelling at Birkbeck, University of London.
Full time. Permanent academic job.
https://www.jobs.ac.uk/job/DRI578/lecturer-in-digital-and-immersive-storytelling
Happy 60th birthday to The Crying of Lot 49, published April 27th, 1966. A strange, hypnotic novel that fascinated me as an undergraduate.

Newly released letters reveal JD Salinger’s wariness over ‘second-rate reviewers’
https://www.theguardian.com/books/2026/apr/26/newly-released-letters-reveal-jd-salinger-wariness-second-rate-reviewers
Today, I am revisiting Packer, Abel L., ‘The Pasts, Presents, and Futures of SciELO’, in Reassembling Scholarly Communications: Histories, Infrastructures, and Global Politics of Open Access, ed. by Martin Paul Eve and Jonathan Gray (The MIT Press, 2020), ... 🧵1/2
... https://doi.org/10.7551/mitpress/11885.003.0030. The significant history of SciELO should be in every scholarly account of the development of open access. 🧵2/2
I have a (cough: several) 8-bay Synology diskstation. I had banked on the failure of one of these devices and so had redundant hard drives to hand and was basically ready for _drive failure_ to be the problem. I have actually just had the power supply unit die and now have a bad fix-it ... 🧵1/3
... job ahead. Furthermore, in my current health state it is extremely challenging for me even to lift one of these devices, which are heavy, especially when loaded with hard drives. I would like to get these data back -- and please do not tell me I should have backed this volume up. I ... 🧵2/3
... could barely afford the primary storage in the first place and, as I say, had prepared for an expected fault... just not the fault that happened. 🧵3/3
Good heavens. The man is totally delusional.
Reading Thomas Pynchon's Gravity's Rainbow as a third-year undergraduate persuaded me to do a PhD and pursue an academic career.
Making friends with library staff during that PhD taught me about scholcomms and propelled me into that field.
This looks an extremely interesting volume, even if the price is a depressing libraries-only rate. Features a chapter by my ex-PhD student Bronaċ Ferran https://edinburghuniversitypress.com/book-transformative-repetition-in-experimental-and-post-digital-poetics.html
Meanwhile, life continues, outside my health difficulties. And at least there is a new tici taci release to enjoy! Duncan Gray - Hollow Point. https://ticitaci.com/releases/duncan-gray-hollow-point.html
Err, hell yes.
With my current condition, the lack of public loos is something that makes it hard for me to leave the house.
(I already know about the disability access card and the emergency loo access, btw)
I am hoping/planning to give my first in-person keynote since 2019 in September. More details soon. I am excited!
But I am being optimistic. I am hoping I will have cleared the chronic norovirus and will not be on parenteral nutrition (IV feeding). I am hoping I will be alive.
This gives me a target at which to aim. You can't actually "fight" the conditions from which I suffer, but whatever level of willpower I can exert, I will.
I won't be able to attend the whole event, as I will need dialysis. But I am very excited to attend one day of it and to speak.
I think it likely that I will need my wheelchair. So beware of being run down!
I could have said "no, I am not well enough at present and cannot envisage being so". But I prefer to say: "I want to do this, but need to be better - I will let you know if things look bad/impossible, nearer the time".
It is strange to me how the terminology of "blogging" has shifted to become, for most people, "writing a/my newsletter". Substack et al. are the cause; it's how they term it. Their ease of use has drawn in many potential bloggers. But most newsletters don't seem to be "news".
The Android Microsoft Outlook app is truly terrible. It gets constantly stuck, not refreshing the inbox. Tried this on 2 devices now. 📩😞
At a time when multi-billion dollar corporations are campaigning to rewrite copyright laws so that they can ingest anything, by anyone into their for-profit systems. It's not technically "theft", but c'mon. "Flagrant disregard of the social contract."
It would be dire for intrusive American legislation to introduce age and identity verification into software used worldwide. I do not want or need my OS - Linux - to know and broadcast who I am.
To be honest, it's a trial too far. I have endured rheumatoid arthritis, vasculitis, primary immunodeficiency, a stroke, pneumonias, end-stage kidney failure & dialysis, fluid overload, and now chronic norovirus & IV feeding. There are people worse off than me. But I also feel I could catch a break.
I am terrified by the IV feeding. If they decide I need this, it will require another tube to be inserted into my neck and then taken out through my chest. But that's not what scares me. I would need to spend weeks in hospital to calibrate the feed and acclimatise. Then I may need to have...
... dialysis in the hospital, instead of at home. This would totally wreck my delicately calibrated life. It would make my work commitments much harder, although it's definitely possible to work during dialysis sessions on the ward. But home haemodialysis is THE aspect that makes my life bearable.
In any case, I have expressed my patient view, to be considered at the MDT, that I want the IV feeding to be the absolute last resort and that we must try to eliminate the norovirus first.
We have some anti-anxiety meds that we hope will calm him. They also seem to be helping.
It is horrible seeing Luka so afraid, but when our trainer was here, he took a treat from my hand. So he'll decompress.
I'm afraid I cannot send any pictures, right now, because I am upstairs, doing dialysis.
Meant to say: Robyn just runs around like a little wriggley pickle - she is hilarious!
It's always DNS
Had another 5 attempts by the hospital to contact me, in the middle of the night, to tell me that I have kidney failure, when I had just finished dialysis.
Ringing me to tell me my kidneys are wrecked, while I am on the kidney-substitute bloodstream un-wrecker device, isn't that helpful.
So, I have done all the tests. Immunology are convening a multi-disciplinary team meeting of renal, gastro, immunology, and rheumatology to decide 1. What to do re. IV feeding (many complications); 2. Whether anti-virals might help; 3. Whether I need high dose immunoglobulin.
The PET-CT should also rule out any more sinister bowel cancers.
The main concern at the moment is the parenteral nutrition (IV feeding). This brings: Infection risk, gastrointestinal tract atrophy, glucose imbalances, liver problems, bone demineralization.
But better than slowly starving.
And another KC Works deposit, at Knowledge Commons!
I have discovered that a well-known English university has promoted someone to the rank of (full) Professor of English, with no book publications, a few book chapters, but no research since 2019. Not appointed by the English dept, afaik. They are a Prof based on admin and the need for a title.
They have some "Second Sick-Leave Deputy Pro-Vice Chancellor for Student Trampolining Activities" title for which, I would suspect, they must interact with the OfS.
I am tempted to go full nuclear on this - naming and shaming - because it really hacks me off. This is all my opinion.
Gaining full Professor was possibly the absolute high point of my academic career and professional life. I worked myself to the bone to make it. I had 4 books, a heck of a lot of peer-reviewed articles, many book chapters. A strong grant record. I was the youngest full Prof of English in the UK.
So, it might sound churlish, but I angrily object to this title - for which I fought and worked so hard, in adverse circumstances of illness - being given out as an administrative label. University embarrassed that it's sending someone to OfS who isn't a Prof. So it makes them Prof.
Side note: I am inferring this all and have no inside information. Also, perhaps some people thought that I was too junior for the title. But I had the publication record.
But what I do belive: this person has no authority to "profess" the discipline of English.
Professor should NOT be an administrative title. I accept that there are such things as teaching professors, who do not have a publication record, but this person is not that, either. Unsure I want to sidetrack this thread into discussing teaching Professorships, but afaik this person has not
taught in the main English department, either, but in the para-degree courses like Foundation Year stuff. Worthwhile work, no doubt. But worthy of being made Professor?
For me, Professor is a title implying some disciplinary mastery, denoting someone who has had some shaping influence on the field.
This does not have to be massive. It is usually VERY specific. But I would expect something. When I hear "Professor", I imagine that this person knows a lot, about a relatively small sub-area of our field.
I do not imagine that they have done lots of admin work with the Office for Students.
Anyway, I should probably stop ranting. I suspect others have different definitions of what Prof might mean. Grants can play a role.
But admin/regulatory Profs with a junior researcher profile in discipline? I am shaking my head.
One more thing: what possible satisfaction does this person derive from this ill-worn and illegitimatly gained title? They must know they are a sham. Yet they will parade around with the title.
The book criterion is also very specific to the discipline I am discussing.
Oh yes, the invisible hand of the market at work, and it's picking our pockets.
https://arstechnica.com/tech-policy/2026/04/internal-emails-show-how-amazon-raises-prices-across-the-internet-lawsuit-says/
I get what a model with this training could do. It could be (even very) useful. But the level of surveillance required, by a for-profit company, to achieve this is beyond creepy. There is nothing about us that can't be quantified and stored, for conversion into $$$.
https://arstechnica.com/ai/2026/04/meta-will-use-employee-tracking-software-to-help-train-ai-agents-report/
I've been reflecting on the challenges of maintaining a blog that's preserved long-term. Balancing the cumbersome process of digital preservation with the ease of instant publishing is tricky, but it's worth ensuring my work persists.
https://eve.gd/2026/04/19/the-necessary-pain-involved-in-blogging-if-you-want-your-work-to-be-preserved-beyond-your-lifespan/
I've been diagnosed with chronic norovirus. This usually clears in days, but I've had it for 4 months due to immunodeficiency. So, I am travelling to hospital in London for an immunology appt, bloods, and a PET-CT. This scan will show whether I can still absorb food or whether I need IV feeding.
In people with a healthy immune system, norovirus isn't a problem. It's unpleasant, but clearable. In immunodeficient people, like me, it's life threatening.
Complete nonsense list. Just the placements of The Merchant of Venice and The Tempest are enough to discredit it.
https://www.theguardian.com/stage/ng-interactive/2026/apr/22/every-shakespeare-play-ranked-lear-antony-cleopatra-hamlet
Sad to see Jisc withdraw the publication router, but it's good that they have released the code (though it should have been open all along).
H/t @davidprosser.bsky.social
https://research.jiscinvolve.org/wp/2026/04/20/publications-router-code-released-as-open-source-ahead-of-service-retirement/
Not sure what I think of this proposal to completely overhaul the governance contract between English HE and the state. All I *do* think is that it is unlikely to happen under this government.
https://post18.co.uk/blood-debt-toil-and-arrears/
US spending on ‘reckless’ Iran war could have saved 87m lives, says UN
https://www.theguardian.com/world/2026/apr/20/us-spending-on-reckless-iran-war-could-have-saved-87m-lives-says-un
87m(!!)
"The Faculty Are the Problem, Apparently"
https://www.thecrimson.com/article/2026/4/20/weld-harvard-faculty/
With apologies, I am in hospital and have had to withdraw from this event. I am extremely sad to miss this. I was honoured to be speaking in such company.
"it is easy to forget how much more opportunity exists in this country for those who are not hereditary elites than in any other nation on the planet."
[CITATION NEEDED]
With reference to my last post: I just remembered that Reclaim Hosting, with whom I used to have an account and who are excellent, offer the option to pay triannually. This would mean that my blog would be available until the end of the three-year period, which is a darn sight better ... 🧵1/2
... than AWS. Unsure what CDL/CDN they have... 🧵2/2
The desire is there, but the convenience to make it work, not so...
Blogging is painful but essential for preserving my work beyond my lifetime. I discuss the steps I take, from metadata to digital preservation, and why it's worth it.
https://eve.gd/2026/04/19/the-necessary-pain-involved-in-blogging-if-you-want-your-work-to-be-preserved-beyond-your-lifespan/
Discovered that Claude code can still access and transmit .env files even when told not to. Discussed some potential security measures using tools like 1Password.
https://eve.gd/2026/04/19/claude-code-can-consume-transmit-and-compromise-your-env-files-even-if-you-tell-it-not-to/
😂
Death merchants move to insider trading on wars
https://www.theguardian.com/world/2026/apr/18/iran-war-bets-ethics-concerns
I am trying Typeless keyboard on Android, and I must say the dictation is absolutely incredible quality. It is annoying that SwiftKey did not keep up, and its voice input is very bad. The one annoying thing about Typeless is that it does not have a full keyboard for spelling corrections, etc.
You are meant to do your corrections by highlighting what needs editing and then using your voice to tell it how to correct that. For instance, "wheel" could be changed to "will" by saying, "Change wheel to will." However, I'd prefer just to do it with a keyboard.
Oh, and I've just seen that it's not directly transcribing, but sometimes even rephrasing what I'm suggesting to it. That is a remarkable discovery that will strongly affect whether or not I go ahead with purchasing it.
It seems in 90% of times to transcribe what I say directly (i.e., dictation).
In the last post that I added, it changed the structure of what I'd said:
1. A sentence starting with, "Yes, this is great."
2. Another sentence starting, "Yes, this is also great."
3. And then, "But..."
My recent threaded post was made possible by the app I whipped up that handles all the social media platforms I am on and will auto-thread a post, with thread counts etc.
Shouts: IT'S ALIVE!!! etc. 😂
I thought I would write with another health update. Thanks to everyone who has wished me well recently. It has been a difficult time. The real challenge that I face is handling an acute problem like this serious dog bite on top of chronic conditions, specifically end-stage renal ... 🧵1/13
... failure with dialysis and rheumatoid arthritis. As just an example, this has forced my dialysis to come off overnight and into three hour sessions, which means that some days I work all day, then just have to set up haemodialysis, do my hemodialysis, pack up and clear up the machine ... 🧵2/13
... and go to bed. I am fortunate that I am able to do this at home at all, but losing the nocturnal temporarily is a setback. Furthermore, because it is a wound causing the acute problem, I have had to come off the blood thinners that my extracorporeal hemodialysis circuit usually uses. ... 🧵3/13
... Obviously, we do not want to antagonize the wound and make it bleed more. But this means that every 30 minutes during dialysis you have to conduct a bolus saline flush to ensure that the circuit does not clot. This not only adds fluid back into me, which we are trying to take out, but ... 🧵4/13
... means the session is highly disrupted. Even reading is difficult, although I would prefer to sleep! Three-hour dialysis sessions are also far more taxing on the body, because you are trying to do the work of days' worth of kidney function in a very compact period of time. So I feel a ... 🧵5/13
... little bit hit at the moment. On top of managing the dialysis and the wound, which is clean and free of infection, thankfully, I also have to contend with a chest infection that has been going on for two weeks. I have different sets of antibiotics from immunology to try to combat ... 🧵6/13
... this. Finally, my ongoing bowel issues are proving incredibly problematic. Since January I have had uncontrolled bowels, apparently due to a norovirus infection, and have lost a great deal of weight as a result. I mean a great deal. This in itself is problematic for infections, as I ... 🧵7/13
... lack the required body mass reserves to fight off new infectious agents. I have all sorts of protein pudding supplements and so on from renal to try to boost my weight, but I am also being referred to the Immunological Gastro Clinic for what they call nutritional work up. That sounds ... 🧵8/13
... fun. So, overall, my health is terrible right now. On top of all this, I am also having to fight with rheumatology to renew my core rheumatoid arthritis treatment, without which I will be seriously unwell. They are quibbling over a slightly deranged liver function test result, which, ... 🧵9/13
... quite frankly, is the least of my worries. Finally, you might wonder why I share this all. First, it is cathartic for me. I have friends who are online, people I have never met IRL, who express empathy and kindness and seem interested to know that I am still here and surviving through ... 🧵10/13
... difficulty. I appreciate that. Second, I think it builds a healthier culture if people feel they can speak aloud of difficulties, challenges, health problems, whatever in this space, without feeling they have to act with a professional mask on all the time. Not every post needs to ... 🧵11/13
... start with 'I am pleased to announce'. Indeed, it's OK to start with 'I am struggling'. We are all people, humans, and we are susceptible to the frailty of our bodies. We cannot but bend to its whims, and to try to make people pretend otherwise is unrealistic. Some people think that ... 🧵12/13
... every illness is defeatable by force of will. It is simply not true. 🧵13/13
I'm interested in reading Gothic-ey/creepy texts about the creation of artificial life (in whatever form that takes), beyond Frankenstein. Do you have a favourite or other suggestions? Got the contemporary Frankenstein in Baghdad already, too...
Worth a read!
Key point made by original poster: "He was struck off for multiple counts of serious misconduct, including lying during an official investigation, followed by working 17 times while suspended, and THEN refusing to engage with the GMC about returning to work"
How much does it cost to peer review grants? Ie how much does selection cost? This paper has the numbers.
https://f1000research.com/articles/15-534
Amusing. I have been sent an invitation to an event promising to take one on a tour of London's lost hospitals I guarantee you, I have seen enough of London's hospitals. Practically done whatever the equivalent is of a pub/hospital crawl.
Here, @ernestopriego.com writes about the ethics of holographic deceased performers
https://ernestopriego.com/2026/04/17/when-the-dead-perform-simulacra-spectacle-and-the-ethics-of-faking-the-live-performance/
Shared some thoughts on our rescue dog Luka. Despite his biting incident, I'm committed to his wellbeing. We've set up safety measures and are working on his anxiety. It's tough, but Luka's progress over the years has been worth it.
https://eve.gd/2026/04/17/thinking-about-dogs/
Special issue of the Journal of Electronic Publishing on "
Open Research for the Humanities and Social Sciences"
I have been thinking about the thoughtful mutations around openness and a more nuanced understanding of HSS practices
https://journals.publishing.umich.edu/jep/issue/456/info/
When I wrote Open Access and the Humanities, a decade and a half ago, OA was very badly understood in our space. I had to make broad brush strokes and assume commonalities of practice.
https://www.cambridge.org/core/books/open-access-and-the-humanities/02BD7DB4A5172A864C432DBFD86E5FB4
The idea of infusing "open" into _practice_ was not something I was able to broach, really. I had to do the Bad Thing and focus on openness of outputs - which, to be fair, captured the tenor of the debate at the time.
But this is why projects like @morphss.bsky.social led by @samuelmoore.org are exciting - the discourse has mutated, because the basics are more firmly embedded now. We can now look at the variegated practices across the humanities and consider where openness might fit.
I feel weak again this morning. Weight is down to 58.2kg - very dangerously low (I should be ~78kg). Immunology are on the case. Nurses are coming to rebandage the wound. I then am seeing GP this afternoon to ensure weekend safety. Then I am seeing the wound consultant on Monday re surgery.
The transparency of "start a war; engineer a ceasefire (you were the one firing); collect a peace prize" is just total brass neck.
Hugh Sexey's Thing

It is remarkable that Harvard can keep any credibility doing this. It's literally soliciting $10m a pop for endowed professorships to be held by people who are opinionated against what the evidentiary approach, in regular professorships, found, because the evidence is inconvenient to right wingers.
Ah! Thank you
Interesting, even though I am by no means a dedicated Stratfordian...
But, frustratingly, all I can find are press releases and news articles about this - no links at all to any published research. Perhaps there isn't any, yet?
One of the changes we are having to implement is that the dogs need to go into kennels, at times. This then involves the kennel cough vaccination for them. The parainfluenza component of the vaccine, sadly, has to be live and so poses a theoretical infection risk to me, an immunocompromised person.
However, after speaking with immunology, I have heard that the infection risk is actually minimal and purely theoretical. I was advised simply to practice good hygiene but that I need not isolate myself from the dogs.
Man, someone in the tech department at Bluesky is having a VERY bad day.
I remember @theblochian.bsky.social live-tweeting my panel, having to fend off the trolls (seriously!), and being both terrified and energised.
It's rare that junior academics get a chance to make political impact, but we did. I submitted written evidence and was asked to speak.
I think that, at the time, open access was seen as a niche science thing and I was the only individual researcher from English - or perhaps, even, the humanities - to submit a statement. Certainly the only voice in favour.
I should reread my submission to see how naive I was.
13 years ago today, with @theblochian.bsky.social, I gave evidence to the House of Commons Select Committee Inquiry into Open Access.
I haven't reread my submission or evidence. I have probably changed my views. But it was an incredible day. I felt heard.
https://publications.parliament.uk/pa/cm201213/cmselect/cmbis/writev/openaccess/m36.htm

We've just been to hospital for my orthopaedic surgery appt. They had booked me into the wrong clinic. This was a wound redressing clinic... It was supposed to be a discussion about surgical skin graft referral. Anyway, a very nice nurse has booked me in for Monday. A total waste of time today.
Semantic search just isn't very good. I have written an OA article and an OA book on this subject, both of which I believe are available to this bot. But it had no idea.

It's going to become increasingly challenging to identify when, in the authorship and publishing process, AI hallucinations were introduced. Mass-scale publishing leaders are as keen for the technology as other CEOs and it means that reference parsing, for instance, could go through an LLM.
Rigorous versioning is, of course, the answer so that we can do the equivalent of the software engineering "blame" command, to find out where. But most industrial publishing manuscript systems do not store the MS in any diff-able format. It's just a binary.
This will, for now, make hallucination hunting, when needed, a very slow and manual process, involving a human trawling through each version of a file, to see who introduced the nonsense...
Interesting new preprint: Cataloguing and theorising open research practices in the arts, humanities and social sciences: Problematising and diversifying ‘Open Science’
https://f1000research.com/articles/15-515
Today is a step backwards. On top of the bite wound, I have a raging chest infection that has not cleared after a full course of antibiotics. Immunology are doing samples to check if it needs targeted antibiotics to avoid a secondary infection.
I am nervous because, last time I was coughing this badly and this productively, I ended up with pneumonia and dissected both my carotid arteries from coughing(!) This caused my stroke in 2016.
So: I am not fully back at work, today. I need to rest to heal and to avoid serious consequences.
Feat Stewart Lee https://www.theguardian.com/culture/2026/apr/15/viral-artists-social-media-videos-stewart-lee-werner-herzog
This seems pretty dire for the Python foundation.
But, tbh, even if I could travel with my kidney failure, I would not go to the USA at this time.
I'd be turned away at the border for my social media posts and/or deported.
Sitting at home with Robyn, who's saying "I'm the good girl who didn't bite you. Please give me treats."
Poor Luka has gone off to training class with Mrs Eve. He has been thoroughly traumatised since the bite incident. He's been shaking with fear when in the sitting room and generally speaking in a bad way.
It's going to take him a while to decompress. Obviously, we are taking precautions so he actually can't bite me or anyone else again. But we also need to calm him down. I'm avoiding eye contact with him to appear non-threatening. I'm also not speaking to him, even though I want to tell him it's OK.
* no "speaking" in that sentence. My dog has not been speaking.

I agree wholeheartedly with Sam. "if your problem with open access is that commercial publishers are hoovering up all the money, design open access interventions that specifically prevent commercial publishers from receiving your money"
The CRUK approach will badly harm their patient advocates.
This group relies on OA to the medical literature and on being able to keep completely up to date with the published findings. They will be the group most harmed by this policy - ordinary people with a vested interest in curing cancers.
The US lost the war. But they can't say that out loud.
https://www.publicnotice.co/p/trump-loses-iran-war
With deep regret, I have had to withdraw from next week's speaking engagement at The LSE. I am afraid that I just cannot guarantee that I will be well enough to speak, after my hospital recovery, or that I will be able to prepare adequately with my current state of health.
"A life saved is not saved for the pleasure of the one who lives it, or the people and communities they touch, but rather for their economic value" - @kfitz.info
https://kfitz.info/humanities-philanthropy-good-life/
A good read on the thorny difficulties faced by OA publishers in the face of the current lack of regulation of AI
https://www.openlibhums.org/news/934/
This is helpful advice, except I'd add: they can easily now add "details" from your book by running it through AI or just asking a model that has been trained on it. It's very easy for them to sound knowledgeable.
It is hard to describe how bad the disconnect is between big tech leaders and those inside AI and those outside it. https://arstechnica.com/ai/2026/04/meta-spins-up-ai-version-of-mark-zuckerberg-to-engage-with-employees/ It is incredible that they think that employees would want to talk to this.
I am back at my desk for part of today. I am discovering that I am extremely shaky as I recover from this latest ordeal. It's hard to use a mouse accurately when your hand is shaking so much!
Really wanted the Flying Mojito Bros album on vinyl, but the postage from the USA is more expensive than the record itself. Double the price.
OK, so long as there remains room and support for new, smaller, and scholar-led initiatives. This is where a lot of "innovation" happens (for all the horrors of that word) and bibliodiversity is important.
Great interview with @elotroalex.bsky.social
https://www.publicbooks.org/courage-or-foolhardiness-talking-aime-cesaire-with-alex-gil/
Nurses have been to re-dress the wound. It's now crackling with electric nerve pain all over the leg. Hopefully, I will not bleed through, again. Have this 2x per week for the foreseeable future.
Contributors must take "full responsibility" for any code
https://www.xda-developers.com/linux-kernel-now-allows-ai-written-code/
Because, clearly, the point of degree classification is social stratification for judgement by corporate employment engines, so everyone should be divided into percentage groups in their cohort... Rather than relative to everyone 🙄
I have to do 3hr dialysis sessions for now, rather than overnight, without any blood thinners. This means administering a saline bolus every 30 minutes. Very disruptive and tiresome. Important to avoid blood thinners when you have a gaping wound, though.
Yes, bombing a country does tend to lead to a lack of trust.
But the very notion of peace talks is ridiculous. Just stop bombing them.

We are also looking into wheelchair accessible vehicles. At the moment, we cannot take my electric wheelchair in the car. It would be useful to do so as, at the moment, I can be driven somewhere, but am then stranded. Anyone with experience of this to give advice welcome!
I did this wrong. I should have used my PIP allowance to get a wheelchair accessible vehicle and outright bought the wheelchair. Instead, I got the chair and will now struggle to afford the vehicle.
Nike used to make these hands-free shoes for people with disabilities called Go Flyease. They have a hinged heel, so you just step in and it locks on your foot. They were max 2 per customer and I bought 2 pairs. The first is now reaching end-of-life and I'm frantically Ebay/Vinted -ing backup pairs!
I can't tell you how good these shoes are for people who can't reach/access their feet - or who have problems with their hands. I'm in the former category and it means I don't need help tying my shoes. Love them so much.
Today's health update: my wound remains extremely painful and I can just about hobble on it. I have surgical assessment on Wednesday. Nurses will come to the house 2x per week to re-dress the wound. Doggy behaviourist coming tomorrow. Bowel remains very troublesome and weight still critically low.
Digital Humanities 2025: Book of Abstracts
https://zenodo.org/records/19494802
Never would have thought that I would be re-posting the Pope in agreement.
The prodigal son returns

I read a lot of Tech news and so decided to pay for a Tom's Hardware subscription. I love the premium content but am surprised that a subscription doesn't remove the huge volume of pop-over advertising that they use. I was hoping to pay so as not to have to wade through these.
"While Mythos might be capable in ways that previous models were not, this appears to be part-marketing, part-truth. For the rest of us, this is just another AI model. For Anthropic, it's an opportunity to gain mindshare and potentially lucrative contracts."
https://www.tomshardware.com/tech-industry/artificial-intelligence/anthropics-claude-mythos-isnt-a-sentient-super-hacker-its-a-sales-pitch-claims-of-thousands-of-severe-zero-days-rely-on-just-198-manual-reviews
I have now had 3 blood transfusions total. They are checking my blood levels now and I should, with any luck, be discharged today.
The district nurses will then come, twice per week, to re-dress the wound.
Specialist plastics team should decide on skin graft surgery soon.
I follow up quotations of others that I am using, to check existence and accuracy, but also use "cited by" if I am reusing something referred to me by someone else and I have not read all of the cited artifact. This hardly ever happens but "cited by" seems appropriate. Lets others follow the chain.
Yum yum hospital lunch!

It is great to see these principles on open monograph acquisition from RLUK.
My only criticism is of "there should be evidence that the initiative is financially viable (or established for at least two years)".
So how are new models supposed to start?
https://www.rluk.ac.uk/shared-principles-open-access-monograph-models/
It seems everything must have at least a two-year grant from a funder. But it's still tricky. I had to sell the benefits of the @openlibhums.org model to libraries BEFORE it was up and running and secure investment so that we could start publishing. Our grant from Mellon covered my time but not...
any publishing activities. It didn't cover the costs of any actual publishing and our plan for the funder said we'd work from day one to build the external economic model, with libraries. Mellon were our godsend for the org. But this RLUK policy could well have stopped us being able to launch.
Many new publishing initiatives are in this chicken and egg situation:
"Are you financially viable?"
"We are not, right now, but we will be, if you all fund us."
So the viability is conditional on the payment that can only be given to "financially viable" orgs in the first place.
This is a really tough one. I don't think many early stage authors could afford to turn this down.
Helen DeWitt turns down $175k Windham-Campbell prize over promotional requirements
https://www.theguardian.com/books/2026/apr/09/helen-dewitt-turns-down-windham-campbell-prize-unable-promote
When the government tells you that we can't afford to give benefits to "scroungers", just remember that they are happy to give £380m to a private business. I can't see they're getting anything in return. Just a straightforward gift to a for-profit endeavour. https://www.theguardian.com/business/2026/apr/09/somerset-battery-factory-jaguar-land-rover-government-funding
There is a child here on the dialysis ward and I always feel terrible seeing it. Yes, I feel frustrated that my kidneys were destroyed in my thirties, but she has had so much less time without dialysis than I did.
Texas court overturns sentence for man on death row for nearly 50 years
https://www.theguardian.com/us-news/2026/apr/10/texas-death-row-sentence-overturned
May be subject to making it out of hospital, but I hope to speak at this.
Warning: child sex abuse.
Afrika Bambaataa, Often Called the ‘Godfather of Hip-Hop,’ Is Dead
But he leaves a totally tainted legacy, owing to allegations of child sex abuse and losing a civil case on this matter.
This completely overshadows any artistic legacy.
https://www.nytimes.com/2026/04/09/arts/music/afrika-bambaataa-dead.html
I find it very hard to listen to Leftfield's "Afrika Shox", featuring AB, without thinking about this.
Good on the technicalities of the new S3 Files option at AWS
https://www.theregister.com/2026/04/09/aws_s3_files_stress_test_corey_quinn/
Shout out to all blood donors with a huge thank you. I am having a blood transfusion right now as my haemoglobin has dropped to 63 (normal: 130-180). Another tomorrow.
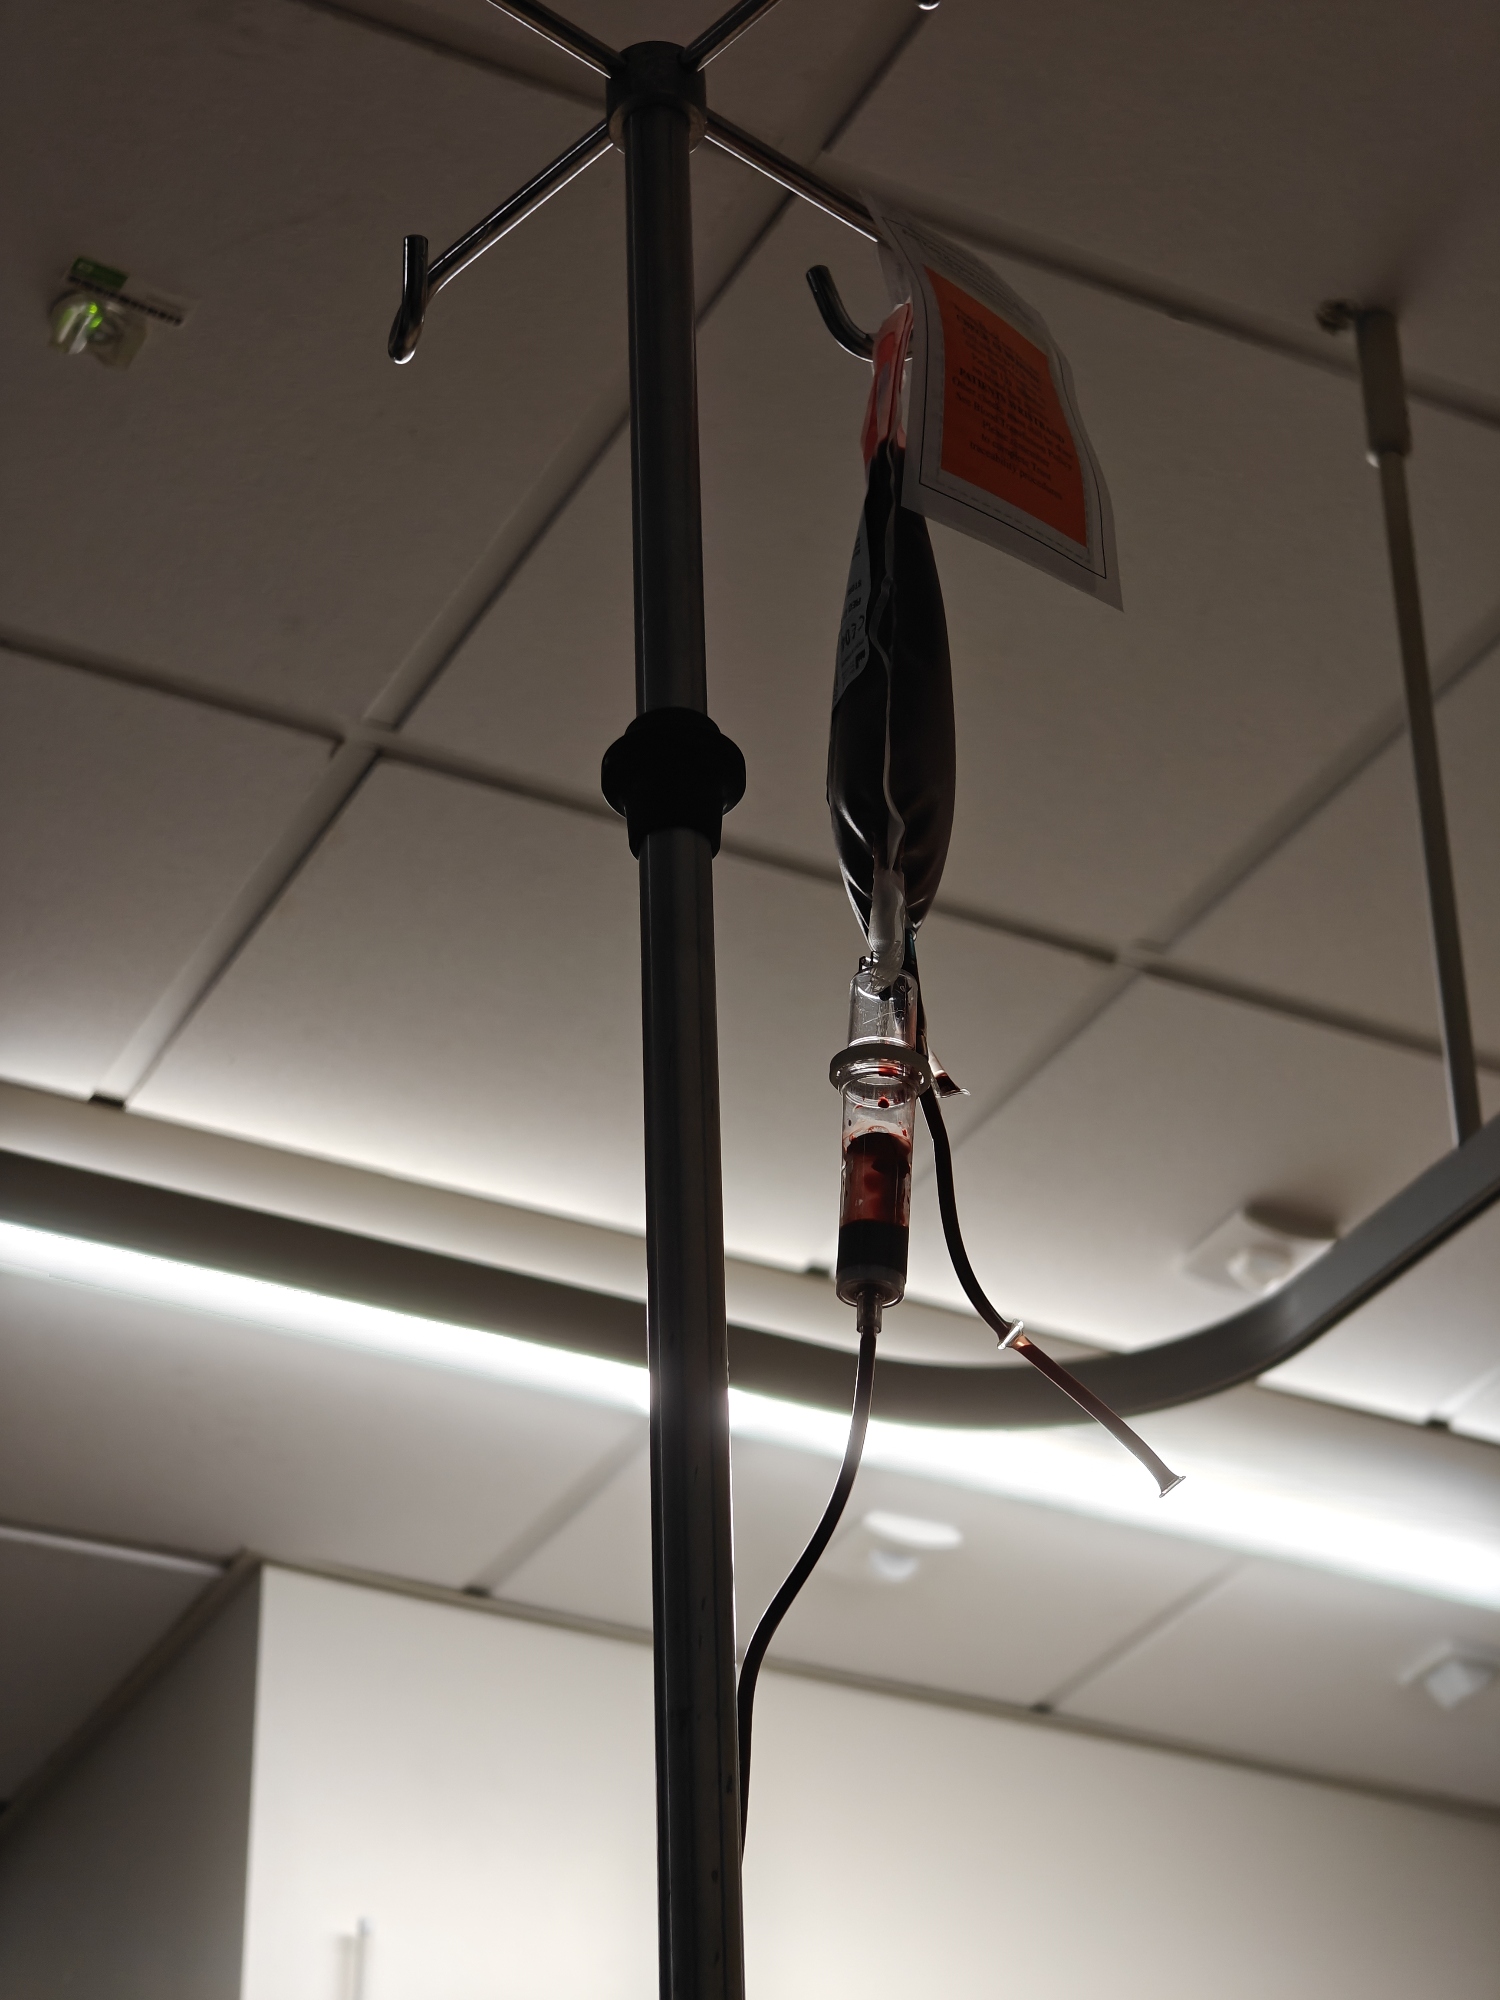
Yes, confirmed: I must return to the Surgical Assessment Unit at the hospital as I am rapidly losing blood. They may accelerate a skin graft/transfer to London. Or they might just re-dress it. Unsure at present.
But it's either that, or he spends the rest of his life in a cold, miserable shelter in Bosnia. I couldn't bear it.
Doing dialysis now, but the wound has bled through the surgical dressing from yesterday and it may be back to the ER/A&E once dialysis is finished. Luka has no idea what he has done/how bad it is.
"Conflict-prone zones" is the new weasel wording of "areas that America and Israel fancy attacking".
It was remarkable today. For the first surgery on my leg, I had a sedative and a nerve block.
I remember just closing my eyes and then hearing "it's done". I was thinking "oh, they've 'done' the sedative administration", but no, the whole procedure had been done.
Has the creator of Bitcoin been unveiled?
https://www.tomshardware.com/tech-industry/cryptocurrency/british-cryptographer-adam-back-is-the-secret-creator-of-bitcoin-claims-new-report-back-refutes-investigation-says-parallels-to-satoshi-are-just-a-coincidence
We had a tragedy yesterday. Our dog, Luka, bit me. Not a small nip, but a proper bite, lacerating my leg down to the bone. He just became so, so hyper-excited by the doorbell and then he took a huge lump out of my leg. I am in hospital now and have had a first surgery to clear up the wound.
I will, with any luck, be discharged tonight, so I can get dialysis tonight at home, although it's going to be on an unusual schedule as I am still waiting for the nerve block to wear off.
As for Luka... We've had him three years and he's never done that before.
He cannot be rehomed now that he has bitten someone like this. He would have to go back to the shelter in Bosnia, and I just couldn't bear it. No sofas, no tummy rubs, no Mrs Eve (the love of his life).
Anyway, we have a plan, including muzzles, lead at all times, kennels when Mrs Eve goes away, and more.
I don't want to lose Luka, even though he bit me.
Bombing infrastructure is totally sick. Hospitals, for instance, rely on power and water. Short-term generators can only last so long. Without supplies, they have no meds. You are killing those with cancer, kidney failure, and heart disease - taking away their final moments on Earth.
While we misrecognise some evil, which can be banal, per Arendt, we also just do a bad job of using the term "evil" often enough, in the face of disgusting behaviour, like this.
Also, just saying "it's illegal" will stop nothing, because nobody is standing there with a stick to enforce such law.
I kindof object to that "brilliant but troubled" label. He may have been troubled; I don't know. But this sentence makes it sound as though he committed suicide because he was "troubled". Rather than, you know, being viciously harassed and threatened by overzealous legal prosecutors.
All the components are in place


Of course, the unsettling red coolant makes for a fun game of 'dialysis machine or PC?'
One of my sisters-in-law helped me rewire my office and music studio. Not only is it all functional, but I can see my pretty PC internals in all their glory!

This is cool! But the same color under different lights (even just brightness) will give different results in the app...
Have had a most enjoyable "onboarding" experience with the Green Party. Invitation to local monthly meetings... Which are all accessible online; a most welcome feature, given my health issues.
The only challenge is a scheduling conflict between this meeting and Luka's dog training...

Needed to create a fictional citation showing how HTML tags might end up in someone's user profile... Eve, Martin Paul, '<blink> and You'll Miss It: Doctor Who, Weeping Angels and the Web 2.0 Era' sounds like a great article that I should actually write...!
C'mon Leo - these nuns-on-the-run are excellent!
After yesterday's ambulance fiasco, I've been dragged into hospital for an iron infusion today. Hopefully this will help stop my terrible narcoleptic tendencies due to severe anaemia.
Just appalling/sick. Surveillance forced upon people with disabilities coupled with threats to withdraw their independence. https://www.bbc.co.uk/news/articles/c203n6qx3ego
h/t/ @ernestopriego.com
I enjoy @ernestopriego.com's enthusiasm for his teaching, his interdisciplinary approach to comics, and his writing about the guest lecturers he brings in
https://ernestopriego.com/2026/04/01/speculative-comics-to-imagine-and-question-technological-futures/
A sad day, indeed, the 1st of April.
I can scarcely believe it's over 10 years since I was sitting at a café in the Netherlands with Johan discussing this. Then we did it. And all hell broke loose.
https://www.openlibhums.org/news/930/
Oh dear. That is not how I wanted today to begin. 6am: blue-light ambulance rocks up outside the house. I did a blood test last night before dialysis and it turns out that I am so anaemic - thanks, kidney failure! - that they wanted to take me straight to A&E.
I did, in fact, already know this; low HB was due to a cock-up by the kidney team taking me off my EPO hormone replacement. So Mrs Eve sent them on their way with apologies. But both alarming and reassuring that they just turned up!