
September 2026
First task of the day is to find a way to get onto my Tailscale tailnet, with an exit node, on a seemingly very locked-down eduroam connection.
Also, I'm totally over the moon to say that the Lever Press publishing board approved my Star Trek Voyager book! This has moved into production for publication in autumn/fall next year.
I made the transfer to St Mark's successfully! There were many bumps along the way, though, and I did not get dialysis yesterday. I must ensure this is sorted today.
"Martin Eve, charged with being an accessory to murder, was executed by hanging." Eek! https://www.theguardian.com/us-news/2026/sep/28/tennessee-woman-execution-christa-pike
Impossible to say how much I hate G4S and the NHS's private outsourcing to them for patient transport. They are now 3.5hrs late. Booked for 6:30am, I woke up at 5am to cater for this. I must arrive between 10am and 2pm, which are the admission times. I also require dialysis upon arrival.
Then, at 9:15am, G4S called my ward to ask what type of transport I might need, such as a stretcher or one with a chair, or would a private taxi do? They do caution that if I need a stretcher it "could take quite some time".
They're already 3hrs late! What do they mean it could take some time? This was booked days ago. 3hrs after they were supposed to turn up, they're phoning to confirm the type of booking I need.
Also, the whole point of it being a G4S ambulance is that I have ongoing chronic type 7 diarrhoea. I don't think a private taxi guy is going to be particularly happy if I have a massive accident in his car, is he?
They should fine these bastards and strip them of their contracts. Nobody has a good word to say about them. I've had to use them before and told myself I would not get stressed by delays this time. I am being sorely tested on that front.
It would be a grave untruth to say that the transfer to St Mark's Hospital is going well.
First, the transport's 1.5hrs late, so far. I didn't really expect any less, having had the "pleasure" of relying on G4S before. It works really well, this outsourcing to for-profit companies.
But worse are the transfer notes for St Mark's, and the medication list therein. The list is totally inaccurate. It features:
* No Prednisolone (leads to my death by adrenal crisis pretty quickly)
* No Buprenorphine (that would be a fun one for me to have to argue to a new medical team: please prescribe me this strong opioid medication)
Many other omissions, dosing inaccuracies, and superfluous medications. This is totally unacceptable and unsafe.
Anyway, I've been kicking up a fuss, and my lovely nurse has got the on-call registrar to amend the list. She has added the buprenorphine patches and tablets, but is unwilling to add the prednisolone.
My nurse said, 'But it's totally unsafe to stop a patient at the dose of prednisolone that he is on. You can't just stop at that level.'
And she said, 'Yes, but I won't prescribe it.'
So now I need the proper medical day staff to fix this.
**This is why I don't trust them an inch with my medications.**
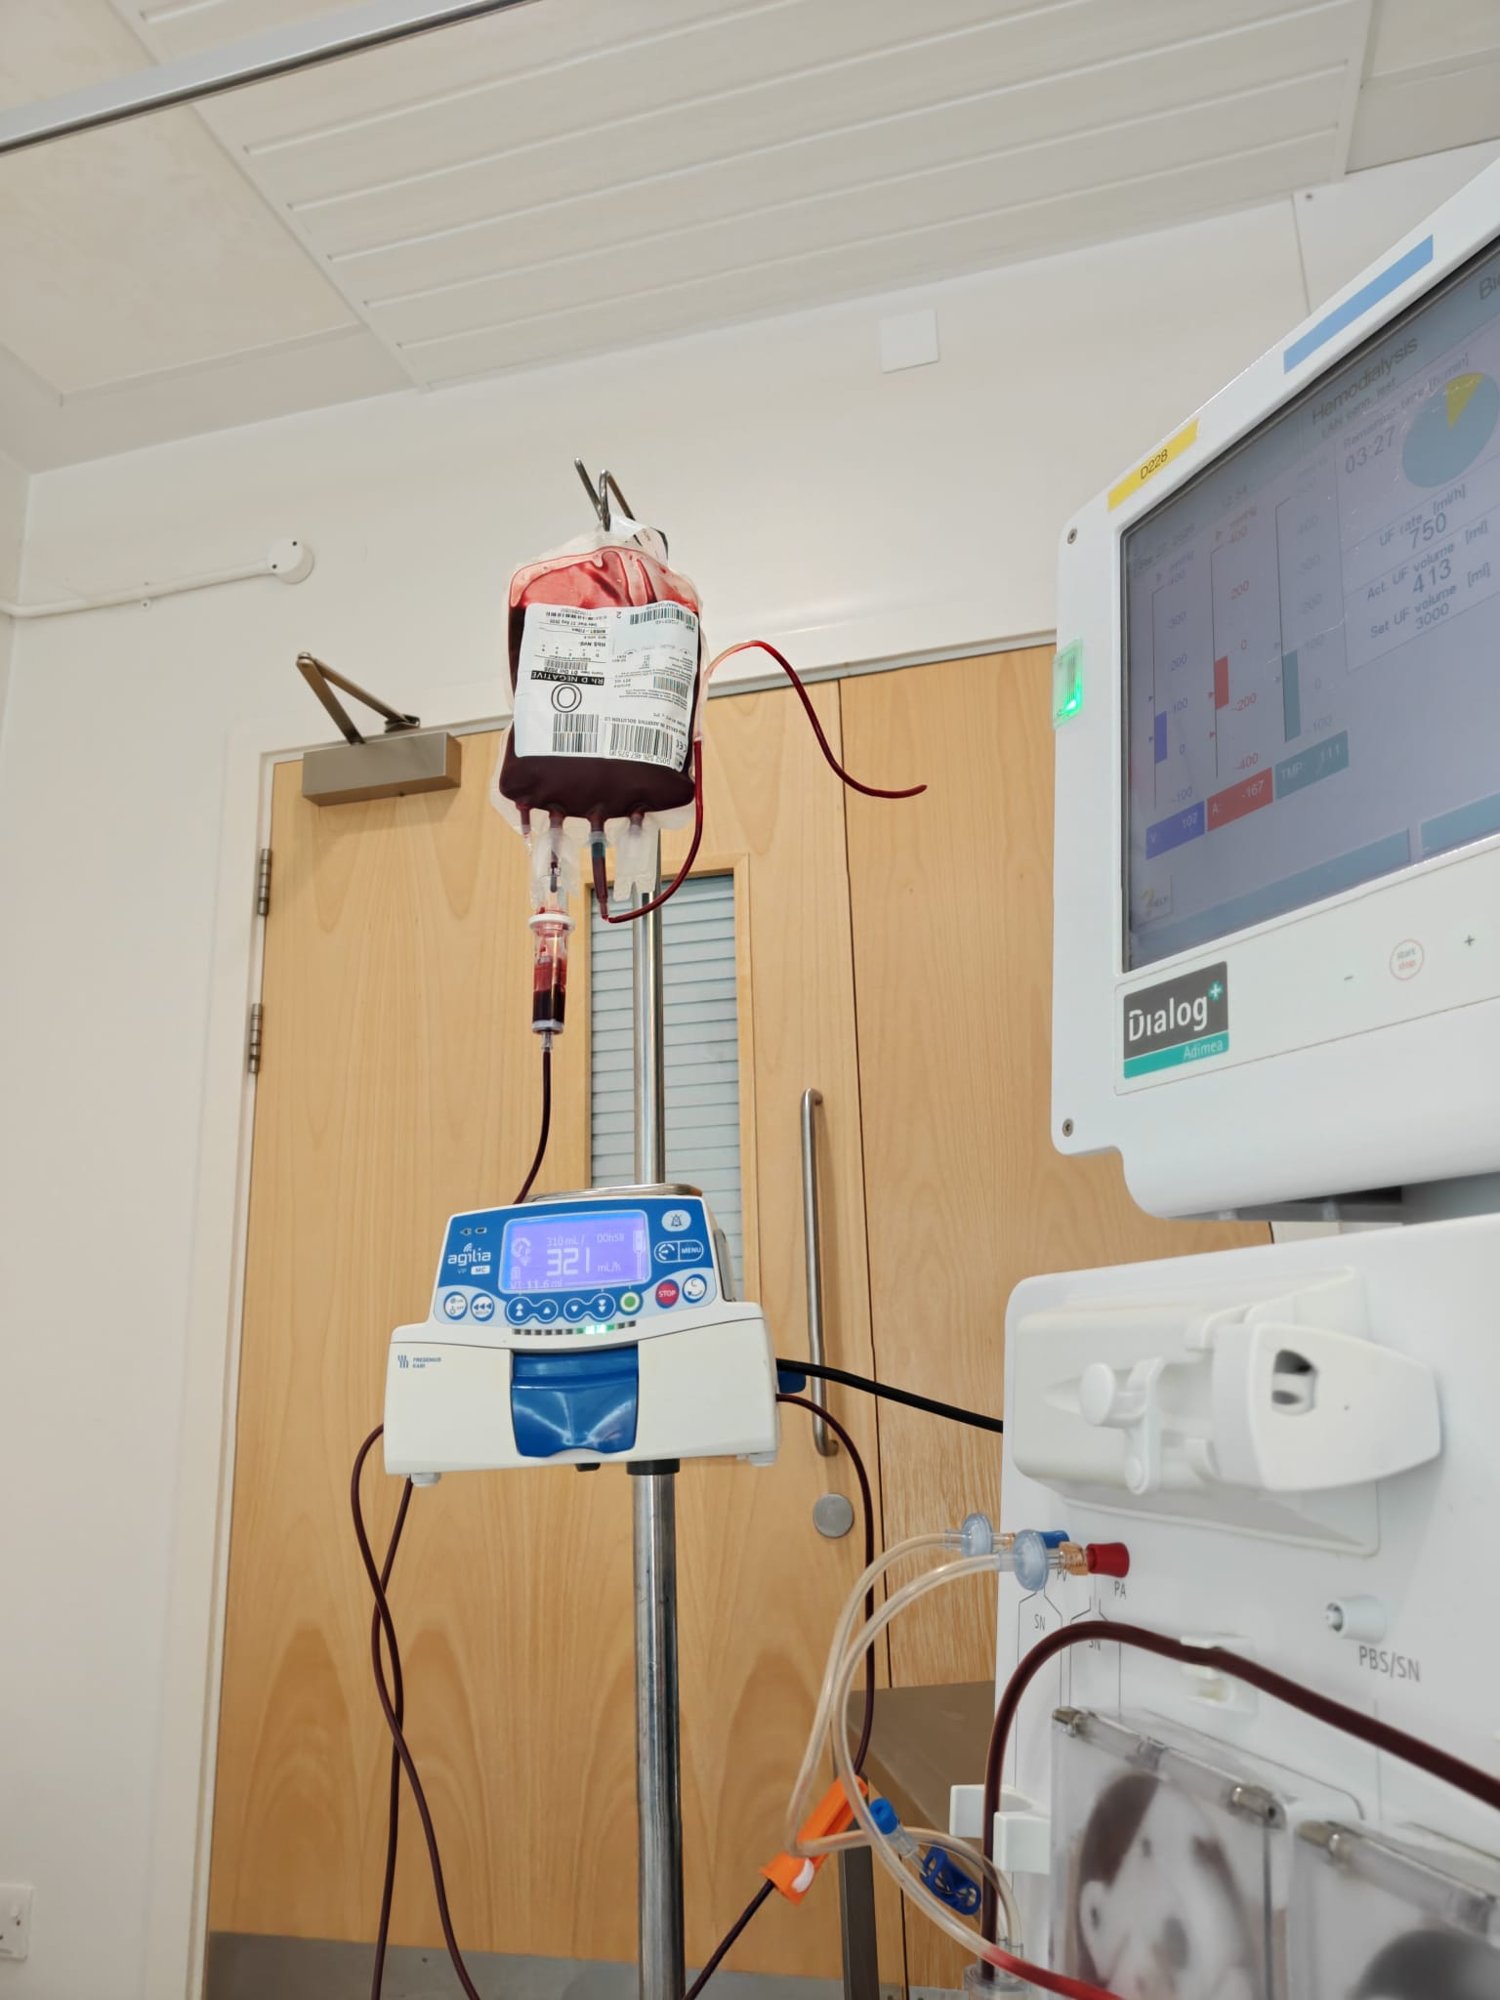
Ready for tomorrow's transfer to London. It will be a bit like this, I imagine.

Blood transfusion -- Blade vampire squad -- underway.
Contrarianism Gone Mad - by Adam Kotsko https://adamkotsko.substack.com/p/contrarianism-gone-mad
TIL: Tella is an app to help journalists be stealthy when documenting human rights abuses. https://tella.app/
I'm working this weekend on digital preservation structures at Knowledge Commons. This is because tomorrow, at ~6am, I will be transferred to London for the next treatment stage. Hurrah! Just a fortnight later than planned, though.
Trying to understand Burnham's stance on universities. Research Professional's Sunday newsletter notes that 'he extolled the values of universities, working with local governments and businesses to boost the economy, talking about “developing the triple-helix approach to economic development by entwining business, academia and government”'.
I think he's probably dreaming of AI, but hopefully also the benefits of local universities for regional economies. But History and English, and all subjects hums, do not fit that easily into such an agenda, no matter how much we want to keep claiming economic benefit and so forth. Yes, there is benefit, but it's not at the scale and type that these politicians are thinking or wanting. It's not tech.
And I also feel that whenever we make this argument, we do sully ourselves a little. I still believe in the liberal humanist vision of why we might read and learn about literature and history. Perhaps that is naive, but it sticks in my mind.
I should also say that Britain is a joke when it comes to doing this kind of thing. The UK's AISI, their safety agency, has been blocked from pre-deployment frontier model testing discussions. So no chance of UK involvement in global governance of these systems. Oh, and we also can't build data centres, it seems. Not that I want them to build data centres, but surely this is a massive error. https://www.theguardian.com/technology/2026/sep/24/construction-largest-supercomputer-delayed
I always hope: this is a guy with an English literature degree. Surely he wouldn't pull the ladder up on the generation below?
But it doesn't work like that.
Do we know whether Hugging Face, for example, reported the OpenAI 'rogue' hacking incident to the FBI? I believe that the FBI is supposed to bring hacking cases to prosecution. The problem is, under the current administration, the FBI seems very unlikely to do so.
The Netherlands Built a Nix-Based Linux Desktop Because Microsoft Cut Off the ICC https://itsfoss.com/news/netherlands-dawo-initiative/
I so want to put in an abstract to this call for submissions. It would, though, be foolhardy (in my current state of health) for me to do so. https://journals.publishing.umich.edu/jep/news/253/
'why do some of us fetishise "pure" HTML?... it is polite to reduce ambiguity. It is nice to be precise' https://shkspr.mobi/blog/2026/09/no-errors-no-warnings-no-gods-no-masters-html-purity-is-a-fetish/
TIL: Veilid is a peer-to-peer data-sharing network that provides privacy for all parties. https://veilid.com/
Cool apps already being built on it include Veilamp for music sharing w/ friends. https://veilamp.com/
And Veilpass, a password manager using the network to sync. https://veilpass.io/
'higher-income nations [said] such arrangements would ... jeopardize intellectual property rights' https://www.nytimes.com/2026/09/25/us/politics/us-rejects-un-declaration-on-preparing-for-pandemics.html?unlocked_article_code=1.EFE.fMrR.EWVUCy3AEl0p&smid=nytcore-android-share
You're talking about species-wide endangerment from lethal diseases, and the EU, that supposed paragon of liberal democracy, is worried that cooperation might jeopardise intellectual property rights.
Call for papers for book chapters in Reimagining Scholarly Communication: Frameworks and Trajectories https://reimaginingsc.hcommons.org
Was Star Trek ever actually good? https://latestartrek.substack.com/p/snw-410-what-to-expect-when-youre
The Politics of Open Infrastructures: Power, Governance, and Justice in Digital Knowledge Practices https://www.openbookpublishers.com/books/10.11647/OBP.0528
>
TIL: PRONOM is an online database that provides clear, reliable information about digital file formats https://pronom.nationalarchives.gov.uk/
The new #meta AI is basically a clone of what Manus did. There was some utter fiasco with Meta acquiring Manus and then de-acquiring it, alongside international tensions and god knows what.
But basically, it just looks like they have now copied that approach, which was to give everyone a VM and then run the model inside that.
TIL: the browser's compositor thread won't stop visual rendering in the case of JS blocking https://kciter.so/posts/the-expensive-main-thread/en/
I can't say how angry I am. My rheum dept at a London hospital called me to say my rheumatoid arthritis med had been changed. They hadn't discussed with me! But worse: I'd already failed this medication in 2023. It does not work for me. Had they not read my notes?
You might think that's not a problem and we'll just not do this. But that's not how it works. At all. They told me that they'd begun the setup process, which involves cancelling the local authority funding for my current medication. The way this is done is by saying that a patient has failed that drug. You cannot then go back and have it again.
So now I must urgently find a way to contact the rheumatology department, who do not offer me a phone line or an email address, unlike other departments who treat me, such as immunology and renal. This is a terrifying blunder, as well as ultra-poor communication. I must urgently hope that the funding cancellation has not yet gone through.
It is also not a trivial matter. Indeed, I do not think I can adequately convey to people who have not experienced it the torment and agony that I experience with untreated rheumatoid arthritis. It is not a livable life.
I note also that the JAK inhibitors that control my arthritis so well are very dangerous. Upadacitinib has led to a life-threatening infection in my dialysis line. Its sister drug, baricitinib, led to the virus that destroyed my kidneys permanently.
But if you offered me the opportunity to go back to when my kidneys were destroyed and told me, 'Your choice is: you can take this drug and then you will have no kidneys and need dialysis for the rest of your life, or you can not take the drug and endure the effects of your rheumatoid arthritis without treatment', I would still opt to take the medication. That's how bad untreated RA is.
There's a service here called Patients Know Best that lets you monitor all of your medical tests. I wish it was called Experts Know Lots, Which Is Why Patients Consult Them, But Patients Should Be Able To Know Things About Themselves.
Excellent to have a social stream of #iPres2026 in the background as I am working on streamlining our digital preservation processes at Knowledge Commons 😁
In the past week, w/ infections, my weight has reeached a new low. I am skeletal. This induces major shakes and twitches. I accidentally threw my smartphone down the hospital bed while writing this!
That all sounds quite amusing, but it's actually extremely debilitating.
I really like this Markup from Hell site, b/c it not only shows humorous bad code, but tells newcomers WHY it's wrong https://www.htmhell.dev/
Jisc's digital maturity report on UK HE says they “have moved beyond reactive investment in digital infrastructure”. Hmm. Really? Recent "AI" adoption? https://www.jisc.ac.uk/news/all/funding-and-staff-capacity-biggest-barriers-to-digital-transformation-for-uk-universities-finds-new-jisc-report
Credit to *Research Professional 8am Playbook for bringing this to my attention. I still can't believe that they are bringing this to a close.
Decolonizing the Dead - Roger Luckhurst on China Miéville https://lareviewofbooks.org/article/china-mieville-new-weird-science-fiction-lovecraft-spy/
“The Poetics of Social Forms”: Remembering Fredric Jameson https://www.publicbooks.org/the-poetics-of-social-forms-remembering-fredric-jameson-1934-2024/
I have a copy of China Miéville's new novel on order. It should arrive soon! However, I've really struggled to read long-form books over the past few weeks. The infections seem to mess with my contextualization.
And this China Miéville book, from what I understand, is long form. Very, very long form. I may need to do some warm-up book to get me going!
It seems I have cleared the life-threatening infection in my dialysis line. The IV feeding has restarted. I have never been so relieved.
A Birkbeck colleague writes on the Okapi. This animal features disproportionately in crosswords as a rare fit for O_A_I! https://witspress.co.za/page/detail/Discovering-the-Okapi/?k=9781997461180
A heavy lift. It takes up to 80 mins to complete this survey. I doubt they will get many responses https://docs.google.com/forms/d/e/1FAIpQLSezwjVjPbDdI-ffohsvhg2Yo9Q_FuS6D1fE9gNIr6bRo-rpvA/viewform
The Freudian Triad as Character Structure in Trek https://latestartrek.substack.com/p/the-freudian-triad-as-character-structure
I may get blood culture results later today. I'm trying to be positive, but these frighten me. If E. coli remains, it has terrifying consequences. 4 surgeries. Near-impossible infection control. How do you stay positive with such loomings?
The Research Professional 8am Playbook, my favourite read on higher education news, notes that the Lib Dem conference doesn't have a single session on higher education or research. At least, not in the official agenda.
Health improved greatly. I'm conscious, I'm functioning, and have no fever. The true awfulness seems to have passed. Though my word! I am tired. But I have not had IV feeding all week because of the E. coli infection. I also basically cannot eat, or digest anything. Much hangs on the culture results.
Book Preview: Adam Kotsko, “Political Theology: The Basics” https://adamkotsko.substack.com/p/book-preview-political-theology-the
You know what really bugs me is that big publishers have these formal-sounding contracts with academics for their books and book chapters, but then they have these policy pages that let you do loads of things, apparently, that are not specified in the contract at all. https://authorservices.taylorandfrancis.com/frequently-asked-questions/open-access-books-faq/#open-access-chapters
These things should be mentioned in the contract itself: the green open access policy, for example.
The Register of British Slave Traders. A huge research achievement. https://britishslavetraders.org
I think I need to read the narrative book-form version to navigate it, though. https://www.penguin.co.uk/books/460026/britains-slave-traders-by-pettigrew-william-a/9781847927903
There is lots more interesting information on their about page, and also the required, I think, disclaimer about the word 'trader' and its potential sanitisation of the brutality. https://britishslavetraders.org/about-us/
I continue to see improvements today in my health situation. I have come off the supplemental oxygen and my saturation is very good. My infection markers are heading downwards. I am still being given five different antibiotics. I slept almost all day.
Also, the totally gratuitous Le Creuset Star Trek Galileo Shuttlecraft casserole dish that we bought arrived! https://www.lecreuset.co.uk/en_GB/p/star-trek-collection-galileo-shuttlecraft-rectangular-casserole/SW2067.html
This one is absolutely hilarious and I love it! But I do think that they missed a trick or two here. Why is the Enterprise one not shaped... like the Enterprise? Why isn't the Klingon entry a Bird of Prey? Is it something to do with the thermal architecture and structural resistance of a casserole dish? I don't know. It seems possible. But this one that we got seemed the most "committed" to ST aesthetics, whereas the others seemed more like "it's a Le Creuset dish with a nod to ST".
Anyway, obviously I have not seen this in person. But I have been amused remotely by photograph.

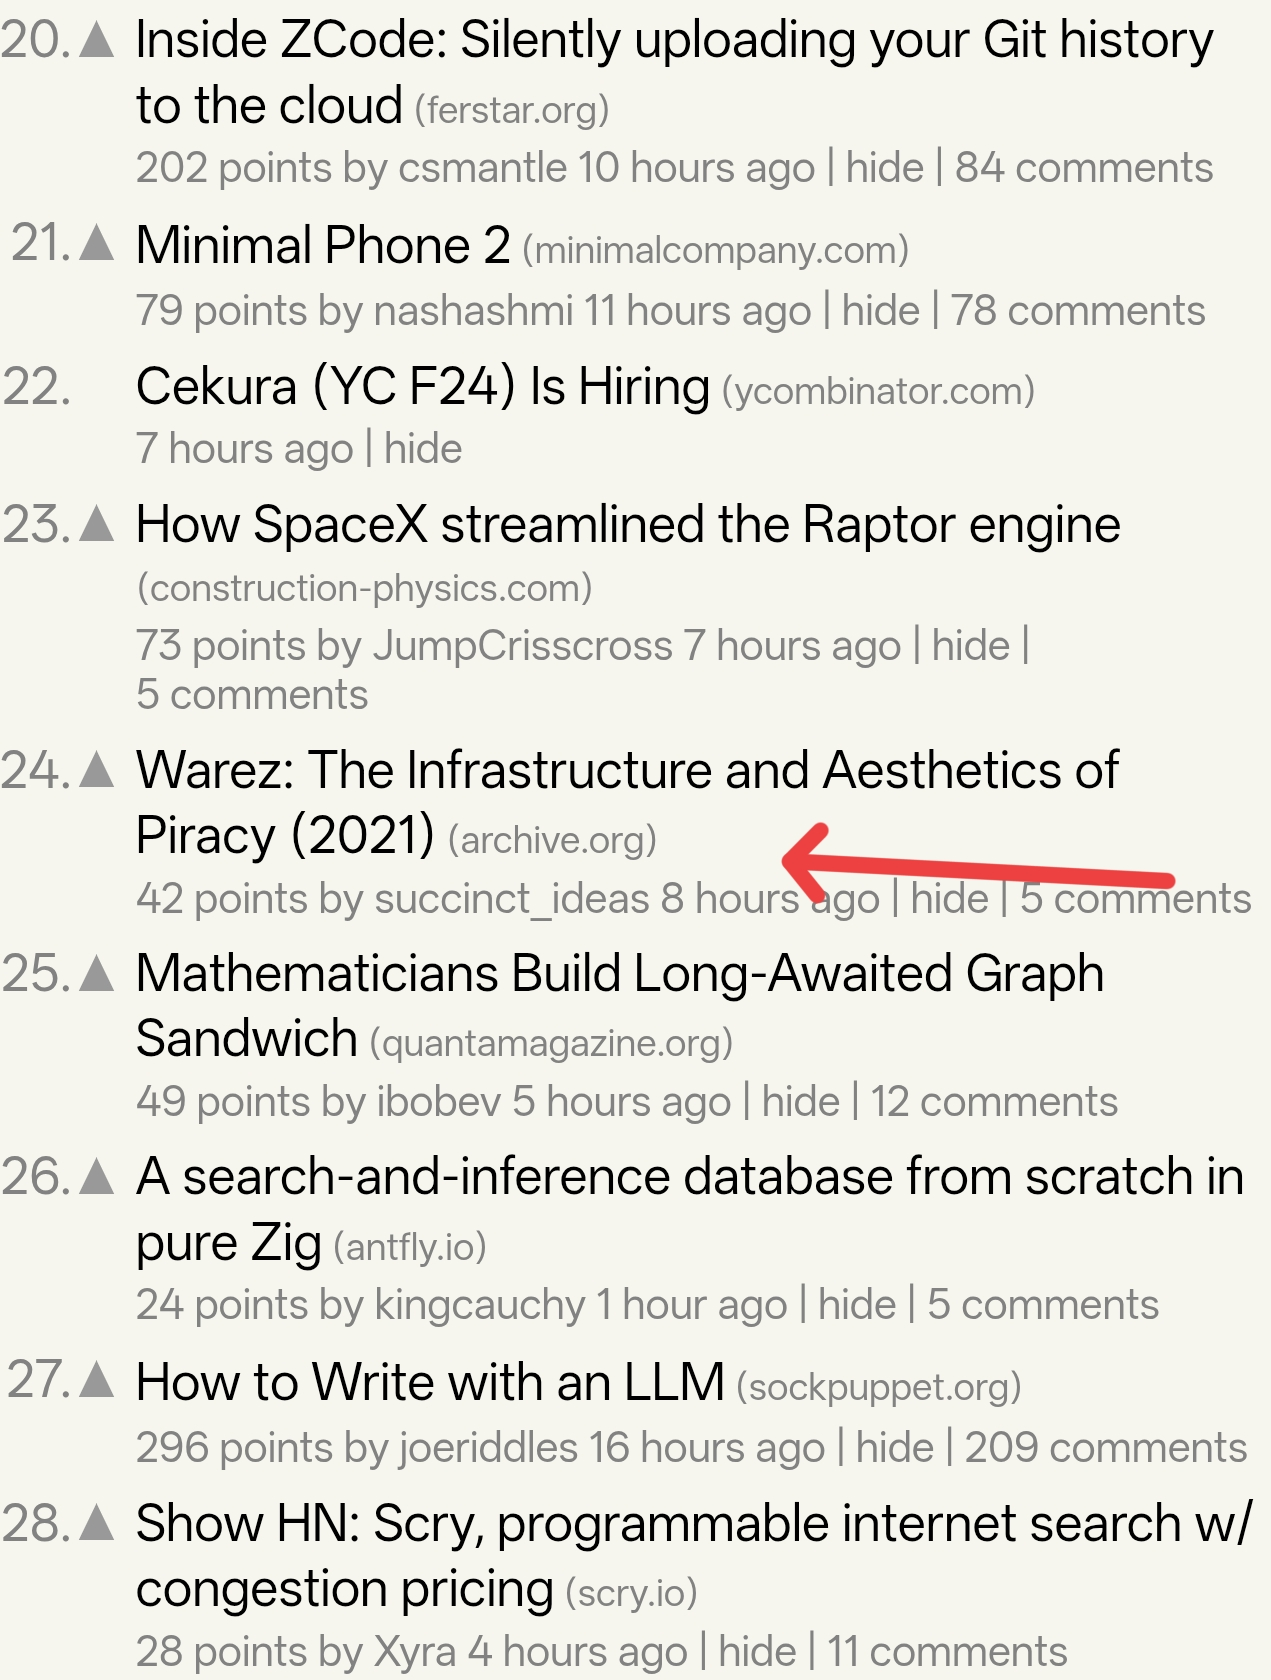
Ha - I made it to the front page of Hacker News! Level-up achievement. Though they all say my book is too long...
"An effective ban on disabled people leaving Britain". https://www.theguardian.com/commentisfree/2026/sep/18/disabled-people-britain-paternalism-disability-services
It is also actually extremely difficult for disabled people with many conditions just to move house *within* the country. It depends upon you being "accepted" by the consultant at the remote hospital. Care transfers can be extremely difficult and complex, particularly if you're on dialysis, I have found. If we move, I will have to redo training courses that take months because there is no coordination between NHS trusts. So your previous experience and evaluation cannot count, apparently.
I have felt a little better today. I did just manage the Fluke album! But it's still very touch and go. I spent most of today, again, recovering, asleep. Hopefully, things are heading in the right direction. But only when we repeat the cultures after the antibiotic course will we know.
On Monday, ridiculously, I thought "I hope that I don't die before Friday, because that's when the new Fluke remixes album is out"! It arrived in the post today early and I am listening now.
To get it to hospital, where I have no CD drive, I asked my wife to open the parcel, put the cd in the portable USB CD drive attached to one of my home servers (w/ video call instructions!), and boot the server. Then I SSHed in, ran the ripper, and pulled it down here using scp. Then I copied to my phone over USB cable. Dedication.
I thought it was worth doing a day early in case the night goes wrong!
The Anthropic class action lawsuit has obviously been hammered with Qs about what foreign taxpayers should do when they have no US SSN or TIN. There's now an update site where you can upload a W-8BEN form. Shame they didn't think of this beforehand.
Diamond Reviewer Pledge is nice. Could do with some tiers, where "Green" (def: inexperienced) is 1 article but "Diamond" is 100% 😂 https://forrt.org/diamond-reviewer/
I use voice dictation to write these posts. It makes me sound much more coherent! My actual speech is v stunted, stop-start, stuttery. I also fall asleep mid-sentence so they take ages to write.
E. coli infection in my dialysis line. This runs via neck to heart area, so infection has life-threatening access. Treating w/ 5 antibiotics. Trying to salvage the line.
Southern Water have commissioned a survey on 'how much you'd be willing to pay to help disabled customers have a reduction on their water bill'. It's seriously just asked me whether paying £4 more per year is very acceptable, somewhat acceptable etc.
This explains an awful lot. The dialysis line, called a central line, goes into my chest, up through my neck, and down towards my heart vessels.
An infection here manages to get straight into the centre of your cardiovascular system. It can turn dangerous and nasty extremely quickly, and lead to total blood poisoning and cardiac infection.
Quite frankly, this scares the life out of me. I know how dangerous this is. I hope my medical team will get this sorted out as soon as possible.
Oh dear. My dialysis line has a bacterial infection. This is what caused my serious incident yesterday. This is the first time in 3.5years this has happened.
Microbiologists say the line needn't be removed. It has to have antibiotics pumped down it, and there's a special lock with antibacterial properties.
Yesterday's nadir was dangerously bad. Today, with oxygen, morphine and IV antibiotics, I managed to read some stuff online in between sleeping. And video chat... "HELLO, YES THIS IS DOG!"

"While Letby’s case has attracted international attention as [a] serious miscarriage of justice..., there is no mention in the ... report of [these] questions." https://www.theguardian.com/uk-news/2026/sep/15/three-babies-may-have-survived-if-hospital-had-acted-over-lucy-letby-concerns-inquiry-finds
This seems reckless. The report says it is not questioning LL, but her managers. But if you take legal guilt as total, even while there are concerns re *actual* guilt, you are taking 2 risks.
I mean, 1 could it not have waited until the Criminal Cases Review Commission had done its work on the Letby case? It prejudices that assessment.
But 2 it's going to look pretty darn stupid should the CCRC decide for review, and it's a miscarriage of justice. This report will then be useless.
I won't speculate on actual (as opposed to legal) guilt but I have followed MD in Private Eye, and it seems very clear that the trial was extremely flawed. This, if anything, needs a serious response.
"The Hugging Face attack was dangerous, reckless and somebody should go to prison for it. If a regular person used massive amounts of compute capacity to hack something, they’d be arrested." https://www.wheresyoured.at/ai-is-already-in-dangerous-hands/
"we need to start arresting people for committing crimes ... because it’s clear that the people running these labs are irresponsible and the people backing them don’t give a shit."
A friend is examining a PhD. They messaged me asking, 'why is it so nerve-wracking?' I think it's b/c if the PhD is good, you face someone who knows more than you about their subject.
Good blog post about the need to serve non-market users. Though I note that the solution here used by The Document Foundation is volunteer labour. https://blog.documentfoundation.org/blog/2026/09/15/lo-268-and-the-languages/
There's a proposed UK social media regulatory bill. By analogy, imagine telling pubs they must ensure "that conversation in the pub is not materially harmful to users;" https://neilzone.co.uk/2026/09/initial-thoughts-on-the-social-media-platforms-ofcom-licensing-bill/
Does anyone know anything about UpCloud? Have they done anything kind of fash recently, like other tech companies? Or are they a potentially more ethical alternative? https://upcloud.com/global/
An article in the LRB defending literary criticism with reference to Helen Vendler. https://www.lrb.co.uk/the-paper/v48/n16/colin-burrow/good-weird-or-bad-weird
Thank you to everyone who replied with kind words about my last post.
I can barely write this update. I feel utterly terrible.
I have clear evidence of consolidation in my lungs, meaning there is another infection. It could have come via either of my central lines, and we're waiting for test results to validate that. All that seems to happen when I go into hospital is that I get infections. Seriously,
The transfer to London that will get me home -- for which I have waited a month -- was called off, as I am not in a fit state to travel.
Everything is spinning. I can't breathe/have extreme pain when I do. I have a raging fever. O2 SATS were terrible earlier.
I am on oxygen, IV antibiotics, and morphine.
If I ran a software program on my computer and "it" hacked into someone else's system, I would be in prison. The same would apply if I ran a small company that did this.
Parchment damage assessment: a review of methods, multimodal workflows, and a transparent reporting framework https://www.nature.com/articles/s40494-026-02899-5
I thought about the "meaning" of damage in Theses on the Metaphors of Digital-Textual History (Stanford University Press, 2024), pp 51-2.
Lots to ponder here, not least how sovereignty might shape a "coherent, well-resourced, globally distributed system" https://katinamagazine.org/content/article/open-knowledge/2026/how-to-build-a-sovereign-global-knowledge-commons
The thread I am tugging at: whose sovereignty? Every distributed node has sovereignty over its info and data and then you presumably have the regional level above that and then the national level and then the international level. How does the hierarchy feed down? Or does basically the open license just mean that sovereignty is guaranteed, at all levels? Presumably there are _constraints_ on, say, individual journals who would be forced to conform to specific standards and practices so that they can fit in the relocation scheme to safeguard material? That may not be bad, but is it sovereignty for them?
Also, cool: "The necessary infrastructure exists and already operates at a global scale. The Public Knowledge Project’s (PKP) Open Journal Systems (OJS) and Birkbeck’s Janeway are open-source journal management software used by tens of thousands of journals worldwide."
This draws a dichotomy between LLMs (acts on training data) & AI (says doesn't exist). Claims the 10% kill-all-humans stuff is false b/c LLMs can't do things spontaneously. But that kind of massacre IS in the training data, via SF! https://pluralistic.net/2026/09/12/god-in-the-box/#llms-are-fake
I mean: Terminator 2, 35 years old now.
TIL: Landlock is a security mod for the Linux kernel that allows programs to restrict their own network/filesystem axx (and other capabilities), at startup, so that if a malicious actor runs code in their context, the blast radius is contained. https://docs.kernel.org/userspace-api/landlock.html
There are various python interfaces to Landlock, but they do not seem well maintained. https://github.com/Edward-Knight/landlock https://github.com/SebastienWae/py-landlock
Does anyone know of any digital dead man's switch system that will:
1. Perform heartbeat checkins (I'm alive!)
2. On fail, after grace period, perform third-party verification of death (He's alive!)
3. On fail (I'm dead. Rats.):
a. Email documents to people
b. Hit a webhook
?
I only just learned, today, about the Institutional Books initiative. Very impressive. https://institutional.org/ https://arxiv.org/abs/2506.08300 https://bsky.app/profile/did:plc:rhqszhuocjmdrtklvxwuyxbv/post/3muz6zb2gtc2j
"The issues the mathematical community faces now are similar to issues that other scientific and creative professions are facing...: how to make sure that, as AI changes the way work is done, we do not lose sight of what that work was meant to achieve" https://mathandai.org/
Critical commentary on Strange New Worlds episode 4.8 by Murray Leeder https://latestartrek.substack.com/p/snw-47-the-care-and-feeding-of-badmirals
Wow. Mark Sample made an ultra-cool WYSIWYG editor for reveal.js slide decks. https://slides.samplereality.com/
I understand both sides of the assisted dying debate. The level of disability hate in our country is so high and many people would face pressure to take this option. https://www.theguardian.com/uk-news/2026/sep/10/esther-rantzen-now-too-physically-fragile-to-end-her-life-in-switzerland
But one thing I don't buy is the argument that "we should fix palliative care first". There's no way that just because you don't legalise assisted dying the government will work hard to fix palliative care. It requires money and the major political parties have decided that no additional expenditure is possible because people don't want to be taxed and because they have agreed to play by a set of fiscal rules that binds their hands.
Then there's me personally. If I have to come off my medications or they stop working for me, I will be reduced to lying in bed in agony all day, every day. Throwing up from pain. In abysmal pain, the whole time. I also worry about an eventual death from kidney failure, meaning that I essentially drown in fluid overload inside myself. These prospects of life and death respectively terrify me, and I know that not all pain can be palliated.
This is why I am a member of DIGNITAS. I want it for me, I am afraid. But the problem is, of course, as per the link above, you will always have to go before you are ready. You cannot afford to be complacent and think, "oh, tomorrow will do". When you've got to the point where things are too bad to bear, it is too late for you to travel, too late for you to take this option.
There was, today, a somewhat alarming (even if, in reality, it was something I already suspected) statement from my immunologists.
Some patients with my immune system problems never recover from norovirus. There have been patients on 24 hour-a-day IV feeding for 15 years.
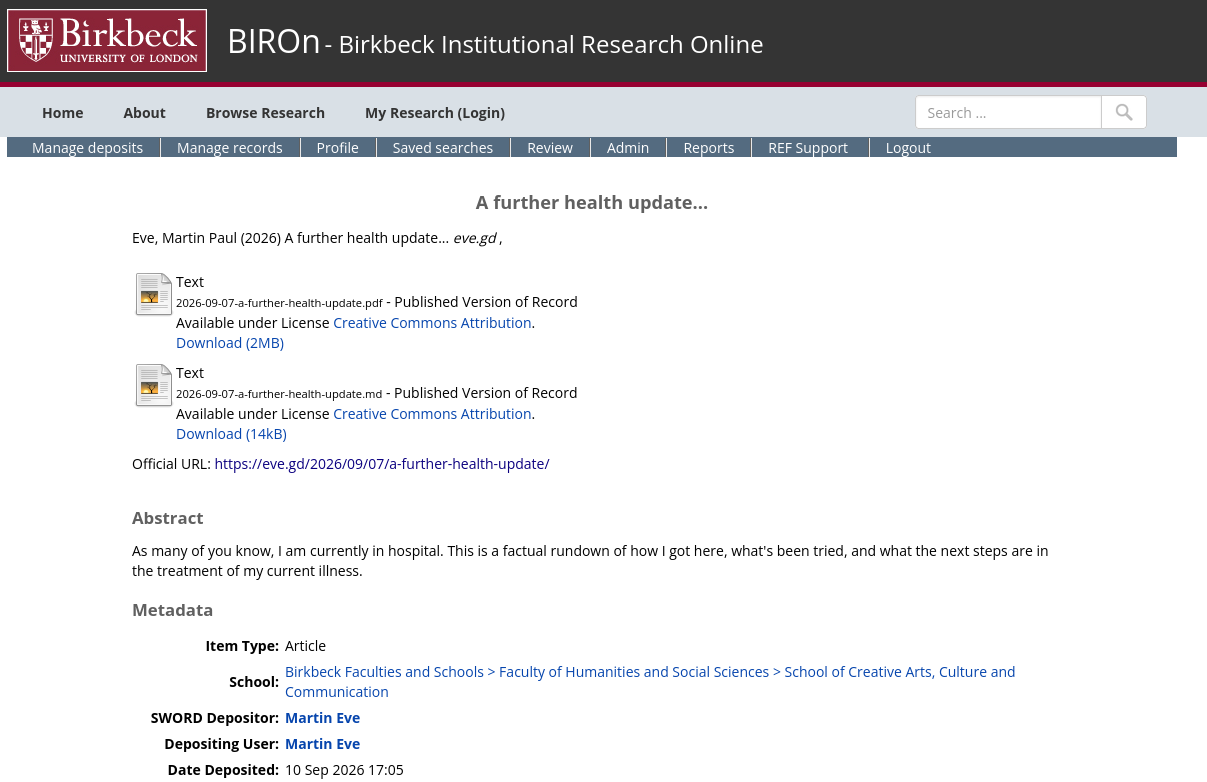
Managed to get my first totally automated submission to BIROn using SWORD working today https://eprints.bbk.ac.uk/id/eprint/57894/
There is a new 20th edition of David Mitchell's Cloud Atlas just published that features a foreword by Gabrielle Zevin.
Zevin's foreword has this footnote. It's a shame she can't get my name right or actually even cite the actual piece(s) in question. But hey!

A friend very kindly made me a cryptic crossword ("The Suboptimal Times Crossword") based on my current situation! I love "Hanging from a limb from Ealing to Epping (7, 4)" [central line]
New Fluke remix https://fluke.fm/discography/faff/a-few-good-days-fluke-remix/
"My estimates of the cost of applications range from €5.3 million to about €43.5 million. Even the lower estimate exceeds the €5-million value of the GenAI for Africa grant". So it cost more just to select who to fund than it will award in funding.
https://www.nature.com/articles/d41586-025-04060-x
If you would ever like a distraction, I wrote a cathartic self-indulgent blog post last night that explains all my health problems clearly, where they come from and why I seem to have so many of them. It also explains what's happening at the moment with my current treatment.
https://eve.gd/2026/09/07/a-further-health-update/
I receive a commission request from Times Higher Education. I note that they do not pay contributors, and that their consideration in the contract is "promotion".

Not now, ancient sheep virus found hiding in medieval parchment!
[I am currently on a social media break (and am hospitalized). I am still writing, working, and posting, but am not caught up on reading at the moment.]
https://eve.gd/2026/09/05/not-now-ancient-sheep-virus-found-hiding-in-medieval-parchment/
[I am on a social media break and posting occasionally]
I just completed the Anthropic settlement form. It's bad for overseas claimants. SSN/TIN won't accept a foreign TIN so I sent them a W8-BEN-E form by email.
Also, you can't reclassify a claimant. We have an author listed as a publisher. 🤦
[I am currently on a social media break. I am posting occasional updates.]
I see an article about an 'illiterate boyfriend test' that involves pronouncing marginally obscure words. A reminder that, if you know what these words mean, but just don't know how to pronounce them, this isn't illiteracy.